
Let’s say that your practice is talking to a new ASC about potentially taking over the anesthesia coverage there. Before you go down this path, you’ll need to know a close estimate of insurance revenue that you can expect to receive by working at this facility. You’ll also need to understand the daily staffing expectations of the facility, to calculate your labor costs and determine your profit margin. In some cases, a subsidy may be required to offset poor payor mixes. Although this equation may seem fairly simple, you’d be surprised at how many healthcare professionals take shortcuts on this first and most important step – determining insurance collection revenue.
12 Months Historical CPT Data
To perform an accurate insurance revenue projection, you’ll first need to request twelve months of historical surgical CPT data. Make sure that you ask for only the CPT codes for which anesthesia was required. Data with local anesthetics and conscious sedation cases mixed in is meaningless to your analysis and will overstate your numbers. If you can’t obtain all the surgical codes with case counts, ask for the top 20.
Base Units
Once you have the surgical CPT data set in hand, don’t make the mistake that many practice managers do – using Service Line Averages to determine average billable units per case. The reason that this is not a sound practice is that anesthesia service lines are comprised of hundreds of different surgical CPT codes and are not granular enough for forecasting. Take, for example, Orthopedics. One site may do open spinal fusions, while another site may do minimally invasive arthroscopic procedures only. The point is, it’s not a “one size fits all” calculation. To do the analysis correctly, you’ll need to crosswalk each surgical CPT code to its respective primary anesthesia code and base unit value, found in the ASA Crosswalk book. Although this takes a little more time, it provides for a much more accurate projection.
Time Units
As far as anesthesia time units go, this is another area where practice managers can perform a disservice to their group by using average times from outdated or generic sources. Don’t use publicly available data from trade journals, as they’re typically based on average Medicare case times, which are overstated. Billing companies are the best source of this data for all payers and should provide it upon request to their clients. Ask for average anesthesia times by ASA code for ASC, Outpatient Hospital, and Inpatient Hospital service locations (yes, they all differ). In our case, we’d use the ASC average case times for our analysis. If you’re only able to obtain procedural times from the facility, you can always divide by 15 to determine your own fractionalized time units. Just understand that this number will be slightly lower than actual anesthesia time, which often begins and ends outside of the operating room.
Units/Case Calculation
Once you have your base units and average time units for each surgical CPT code and corresponding primary ASA code, you’ll then multiply that unit sum times the annual number of cases for the respective surgical CPT code, from your 12-month file. This will give you the annual total units by surgical CPT code, which can be summed and divided by total cases, to determine average billable units per case.

Blended Unit Rate
Last, you’ll need to determine your Blended Unit Rate for the prospective service site. Don’t use your practice’s historical payor mix, as it’s an “apples to oranges” comparison to the site you’re doing your proforma on. Instead, use the payor mix provided by the new facility and multiply the percentage (raw number) of each payor to its respective conversion factor. Use your managed care contract matrix for in-network plans and estimate $45-$50/unit for all out-of-network plans. State Medicare, Medicaid, and Worker’s Comp rates should be fairly easy to look up and populate.
Once you have all your payor values entered, sum the products of all lines. Divide this sum by the payor mix total percentage (typically 100) to arrive at your blended unit rate.

Estimated Annual Insurance Revenue
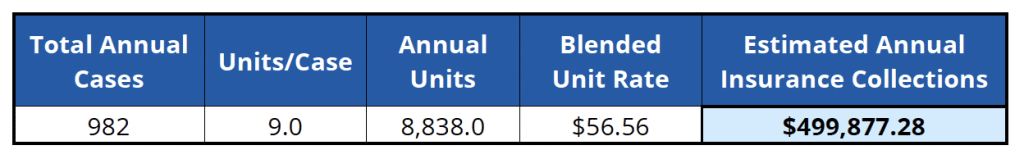
Based on your work thus far, you now have the (a) total number of annual cases, (b) the average billable units per case, and (c) the blended unit rate. Simply use the following formula to arrive at your estimated annual insurance revenue: (a*b)*c. You can use 96% of this number, if you’d like to account for the standard Net Collection Rate.
Final Comments
In closing, don’t use service line averages; use exact CPT to ASA crosswalk data. Don’t use generic or Medicare-specific average times; use site-of-service specific time data from all payor sources. Don’t use your practice’s historical payor mix; use the payor mix provided by the prospective site. I also recommend excluding flat fees (non-time-based procedures) from your estimate, as they rarely make a significant impact on the overall numbers. By taking the time to perform this important exercise correctly, your practice will be able to discern true business opportunities from future loss leaders.

Hal has 30+ years of experience on both the payor and RCM side, with a focus in Anesthesia. He formerly worked as a senior claims approver at United Healthcare, as well as a compliance officer for multiple national anesthesia billing companies. His broad-based experience ensures that MSN clients have a resource for documentation and billing issues. His past speaking engagements include ASA, MGMA, Dartmouth, and Johns Hopkins.


